
LTC’s Story #
LTC is a 13-year-old girl with cerebral palsy. She was born prematurely as a twin; she experienced neonatal hypoxic ischemic encephalopathy (HIE), a condition where her brain did not get enough oxygen, leading to brain injury. She faced health complications, leading to a 29-day hospitalization in the neonatal intensive care unit (NICU). She also has a disease that disrupts the normal functioning of mitochondria, which generate energy in the body’s cells.
She developed cerebral palsy symptoms that significantly impact her communication and movement abilities.
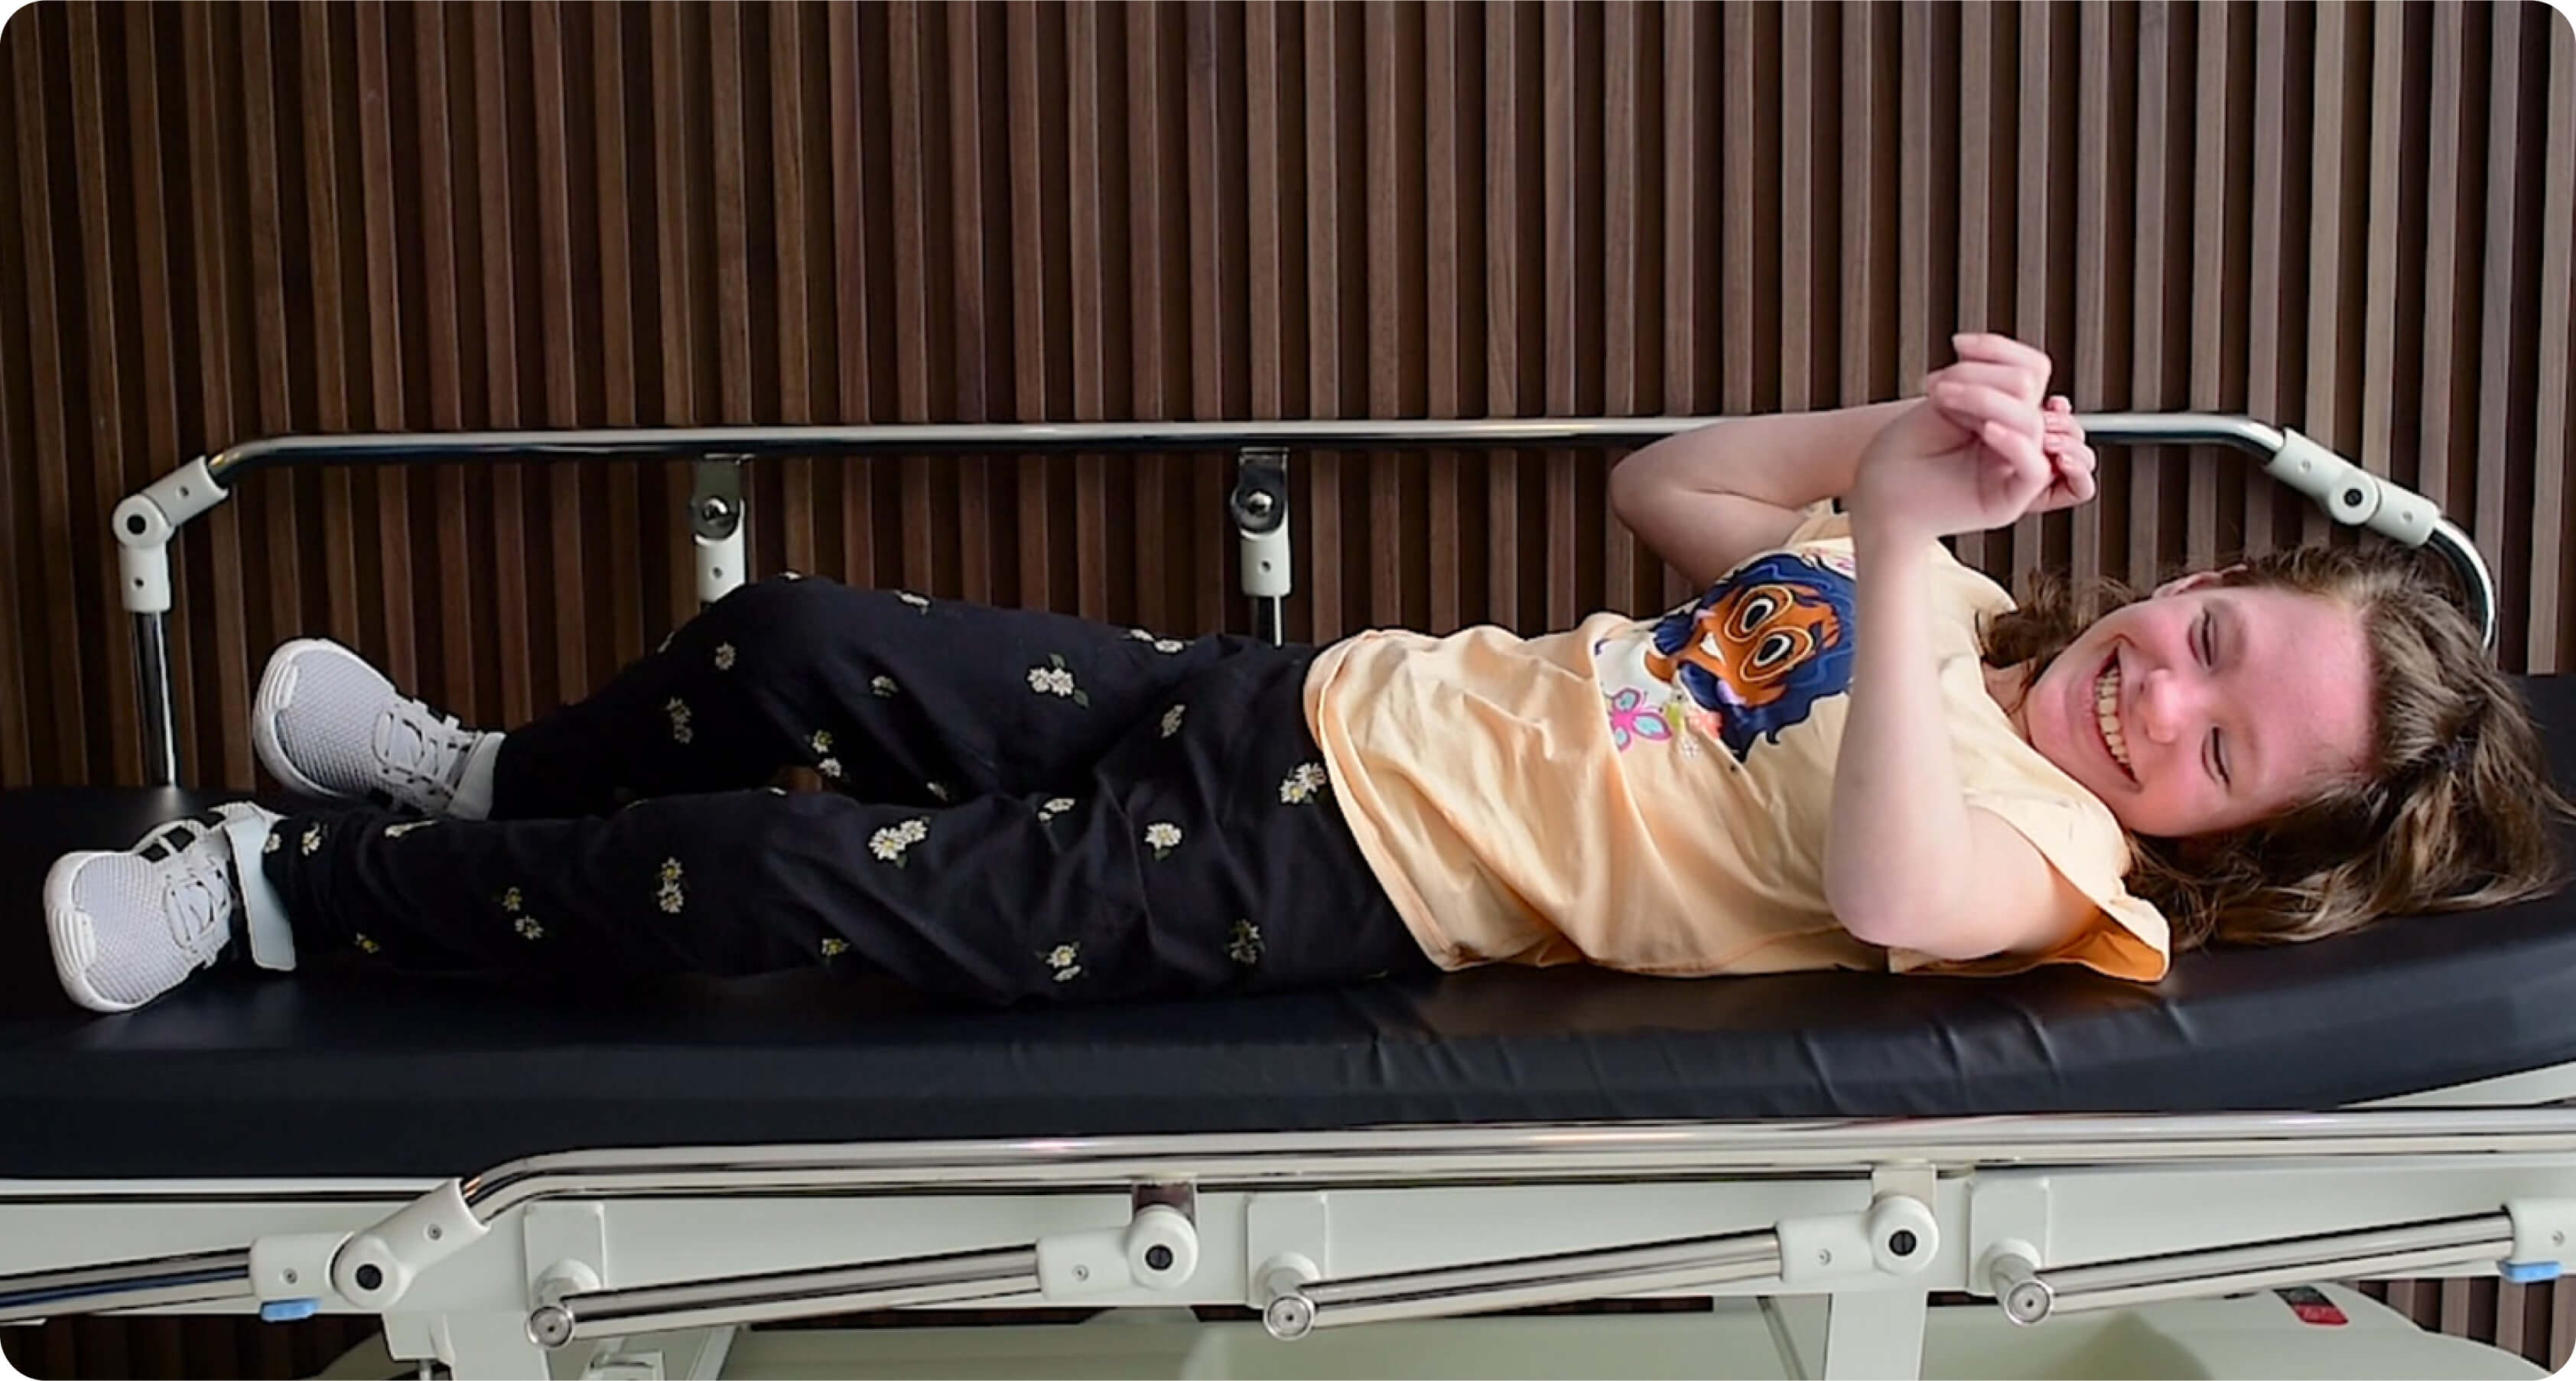
How cerebral palsy affected LTC #
HIE occurs when a newborn’s brain cannot get enough blood or oxygen which kills neurons, the cells of the brain. Depending on how long the oxygen deprivation lasts, and which parts of the brain are injured, symptoms of HIE can vary widely, and may include delays in development, intellectual disabilities, epilepsy (a seizure disorder), cerebral palsy, and heart problems.
When LTC’s parents brought her to receive our protocol for cerebral palsy, our pediatric neurologist described her condition as cerebral palsy with spastic quadriparesis, meaning muscle stiffness in all four limbs. She displayed language and motor delays, with speech and movement capabilities less than typical for her age. She could not say understandable words and could not sit without support.
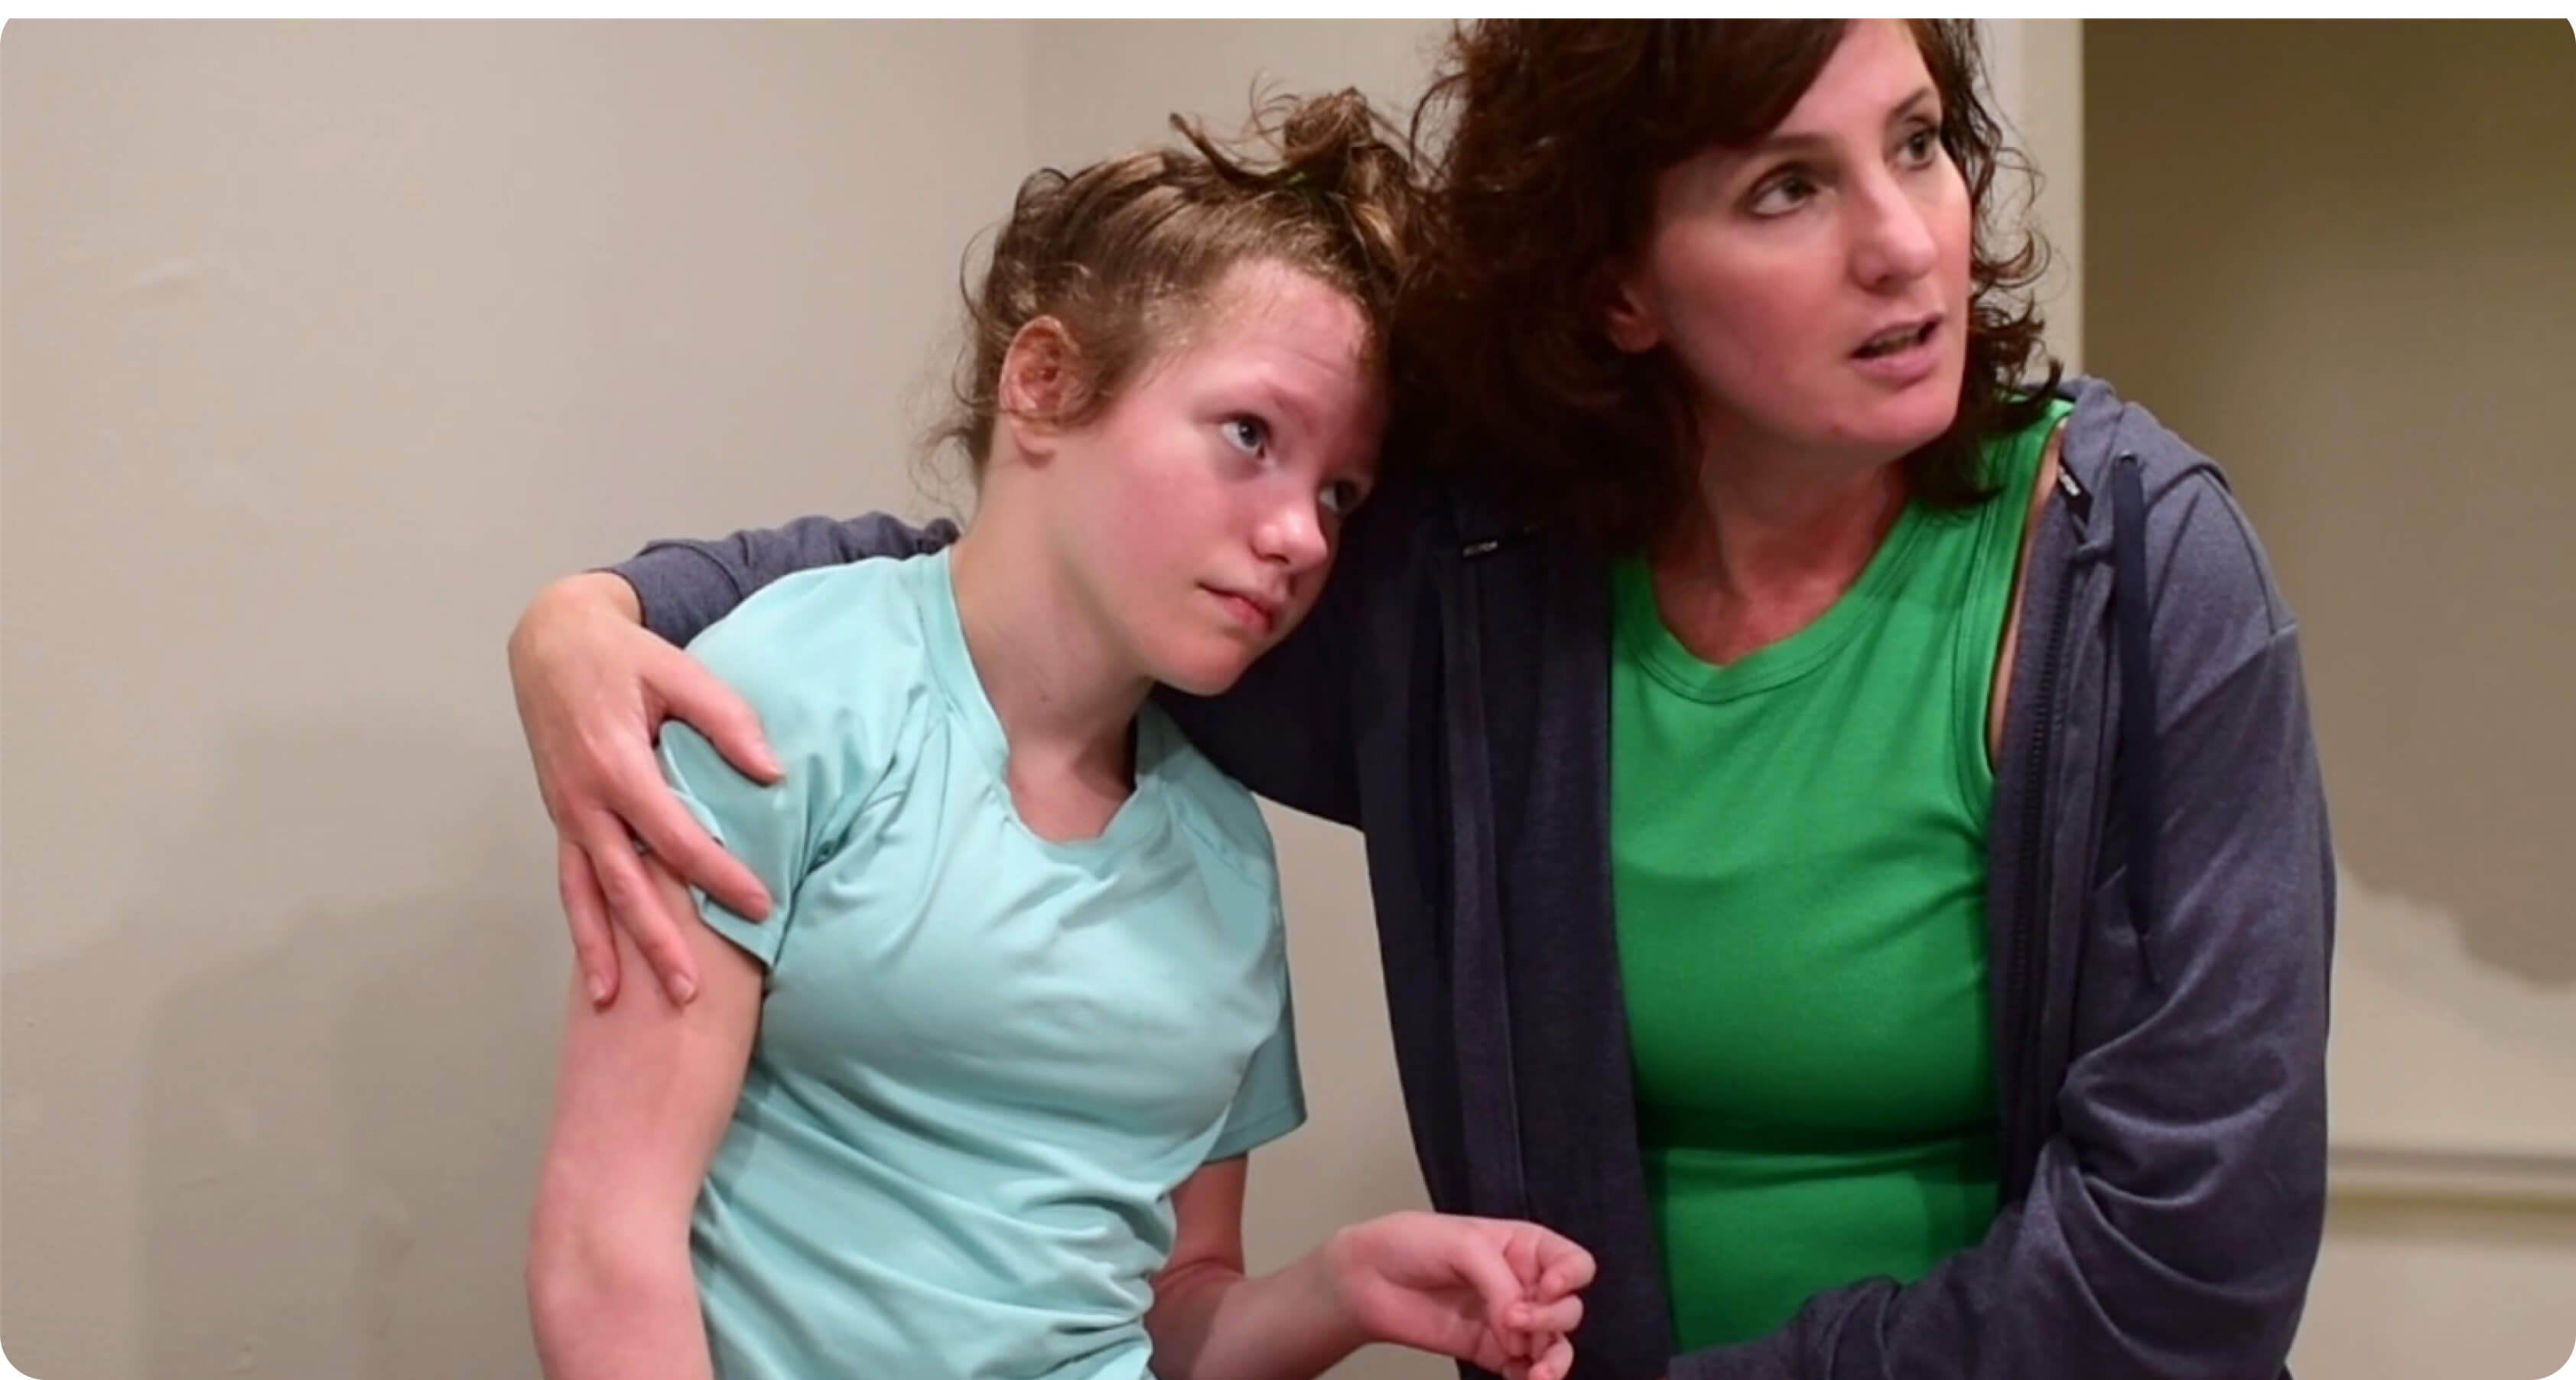
Symptoms prior to receiving the protocol #
Before the protocol for cerebral palsy, LTC’s symptoms included the following:
- Spasticity in all four limbs (spastic quadriparesis)
- Inability to sit without support
- Inability to walk
- No verbal communication
- Poor posture and head support
Cerebral palsy protocol #
LTC came to our Monterrey, Mexico clinical research center, where she participated in an open label clinical trial to explore the safety and efficacy of our protocol for cerebral palsy.
LTC’s protocol followed these steps: #
- LTC received an MRI (magnetic resonance imaging) scan at a local hospital to visualize her brain structure and precisely locate where the radiofrequency signals should be focused.
- Our neurologist tailored the protocol for cerebral palsy to LTC’s specific injuries, and our technicians calibrated the device to deliver the correct dose.
- The protocol was delivered for one hour a day for 28 consecutive days at our clinical center.
- After receiving the protocol, NeuroCytonix monitored LTC for any potential negative effects (safety), as well as changes in motor function, behavior, and cognition (efficacy).
Using special, high-resolution MRI (called diffusion tensor imaging, or DTI) along with a computational method known as tractography, we visualized neural tracts in LTC’s brain before and after the protocol. These neural tracts are information “highways” that connect regions across the brain to support functions like movement and cognition.
Electroencephalography, or EEG, is commonly used to assess seizure activity in children and adults with epilepsy.
To assess LTC’s joint spasticity, we used the Modified Ashworth Scale (MAS)1. This test is given by a trained clinician, who can measure how much the muscles around the knees, ankles, wrists and elbows tighten after the joint is moved.
To examine the protocol’s impact on disability, we used the Pediatric Evaluation of Disability Inventory (PEDI)2 and the Pediatric Quality of Life Inventory (PedsQL)3, survey-based tools that explore aspects of daily life. The PEDI tool assesses the daily functioning of children with disabilities, looking at their ability to do things like dressing, eating, and moving around. The PedsQL measures overall well-being and quality of life in children and teenagers.

Life after the cerebral palsy protocol #
After the protocol, LTC’s tractography images showed an increase in her neural tracts, especially in the corticospinal tract, a pathway associated with movement control. LTC’s EEG did not display any significant changes.
On the MAS, LTC displayed lower spasticity in her right knee, both elbows, and the right wrist after she received the investigative cerebral palsy protocol.

On the PEDI scale, LTC improved in the self-care, mobility, social function, caregiver self-care, and caregiver social function domains. LTC’s PedsQL evaluation showed improvement in pain and fatigue areas.
Beyond these clinical indicators, LTC also experienced concrete improvements in her abilities and quality of life following the protocol, including:
- Greater speed in all the movements she performs.
- Greater strength in both arms, and improved grasping with both hands.
- Better head support and better back posture during sitting and standing with support.
- Improvement in chewing and swallowing of food.
- Cognitive improvement and greater ability to follow verbal commands.
Contact us if you or a loved one are interested in receiving our CP protocol
References #
- Harb A, Margetis K, Kishner S. Modified Ashworth Scale. StatPearls. 2025.
- Haley SM, Coster WJ, Ludlow LH, Haltiwanger JT, Andrellos PJ. Pediatric evaluation of disability inventory. Physical & occupational therapy in pediatrics. 1992.
- Varni JW, Seid M, Rode CA. The PedsQL: measurement model for the pediatric quality of life inventory. Med Care. Feb 1999;37(2):126–39. doi:10.1097/00005650-199902000-00003


